
A cervical steroid injection is an image-guided epidural injection that delivers anti-inflammatory medication near an irritated nerve root in the neck. It may help adults with neck pain that travels into the shoulder, arm, or hand from a herniated disc, bone spur, or narrowed nerve opening when physical therapy and medication have not been enough. Board-certified pain specialists at California Pain Consultants in San Diego evaluate neck and arm pain and perform cervical steroid injections as part of a broader treatment plan.
Cervical back pain can involve an inflamed or compressed nerve root, with pain that travels into the shoulder, arm, or hand. A cervical steroid injection is an image-guided epidural option for carefully selected nerve-related symptoms.
For selected cervical back pain, the medication is placed in the cervical epidural space to reduce inflammation around the affected nerve. It does not remove a disc herniation, reverse arthritis, or replace urgent surgical evaluation when major neurologic compression is present.
When cervical back pain includes radicular symptoms, candidacy depends on the symptom pattern, neurologic examination, imaging, prior conservative care, medication risks, and a clear plan for measuring function after treatment.
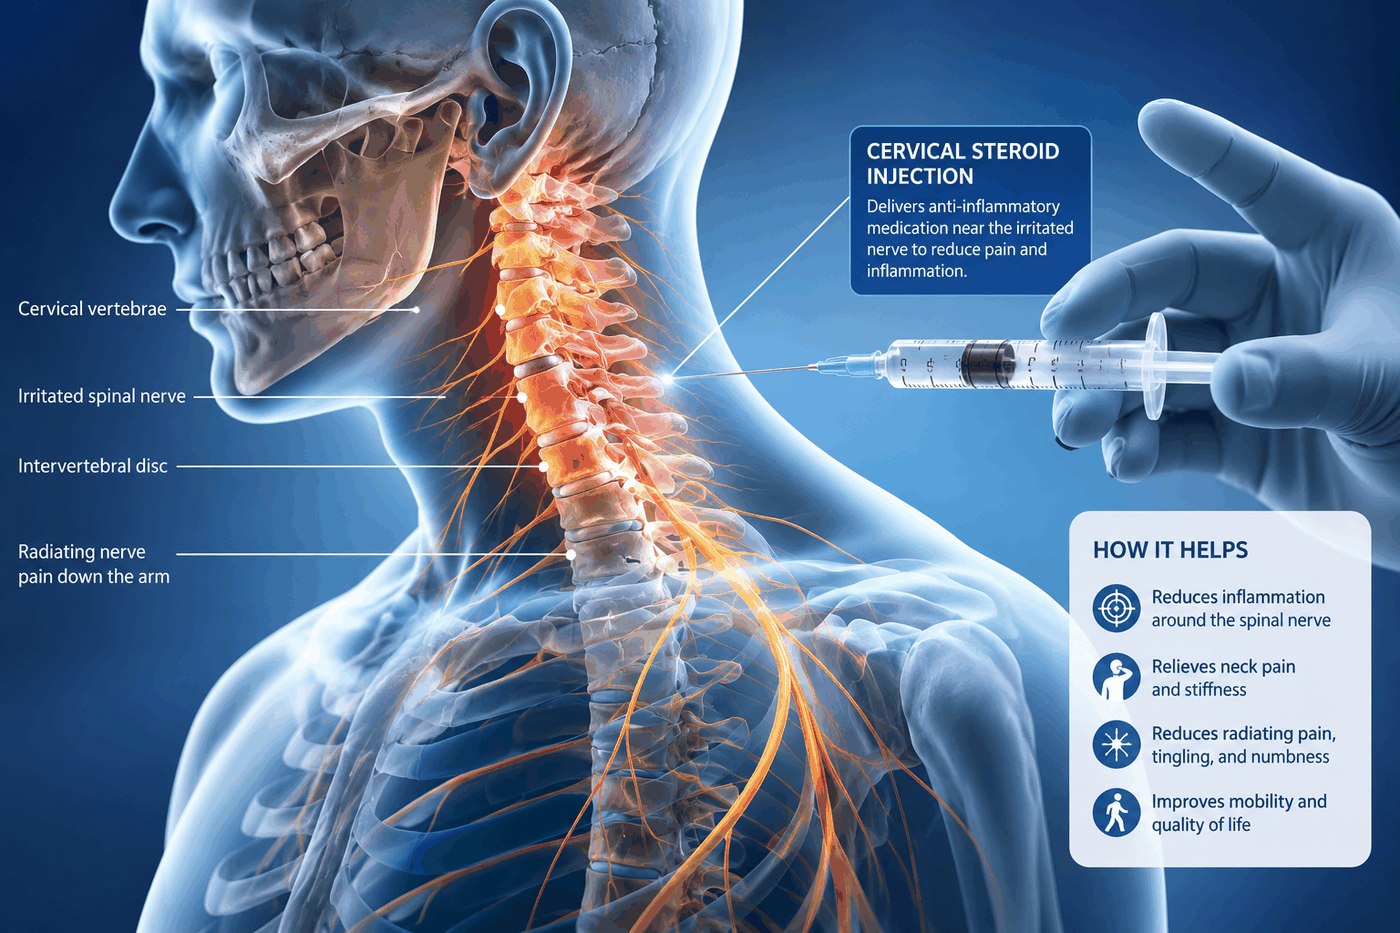
For selected cervical back pain, a cervical steroid injection uses fluoroscopy and contrast to deliver corticosteroid near an irritated cervical nerve root.
What Is a Cervical Steroid Injection?
For cervical back pain with radicular symptoms, the procedure delivers anti-inflammatory medication into the epidural space surrounding the cervical nerve roots. Interlaminar and transforaminal approaches reach the target differently.
Cervical radiculopathy can develop when a disc herniation, bone spur, or narrowed foramen irritates a nerve root. Inflammation can amplify symptoms even when the structural narrowing itself is unchanged.
The neck, or cervical spine, is made up of seven small vertebrae, according to the American Academy of Orthopaedic Surgeons. Nerve roots leave the spinal cord through openings between them, so a disc or spur at one level tends to produce symptoms in a predictable part of the arm and hand. Imaging changes are common and do not always cause pain: the AAOS notes that nearly half of people middle-aged and older have worn disks and pinched nerves that do not cause painful symptoms. That is why the exam and symptom pattern matter as much as the MRI.
Fluoroscopic guidance and contrast help verify the needle position and medication spread. The cervical region contains the spinal cord and major blood vessels, so technique, patient selection, and safety precautions are especially important.
When a Cervical Steroid Injection May Be Considered
The clearest indication is cervical radicular pain that remains functionally limiting despite appropriate conservative care. Many people improve without a procedure; the AAOS notes that the majority of patients with cervical radiculopathy get better over time, sometimes within days or weeks. An injection is generally considered when pain is severe or slow to settle.
Cervical Disc Herniation
A protruding or herniated disc can inflame and compress a nerve root, producing pain and sensory symptoms into the arm.
Cervical Radiculopathy
A consistent pattern of arm pain, tingling, numbness, or weakness may identify a specific affected nerve root.
Foraminal or Central Stenosis
Arthritis and bone spurs can narrow the nerve exit or spinal canal. Injection may address inflammation but cannot enlarge the space.
Persistent Postsurgical Nerve Pain
Selected patients with ongoing cervical radicular symptoms after surgery may be considered after updated evaluation excludes a condition requiring another approach.
Symptoms of Cervical Nerve Irritation
The distribution of symptoms helps distinguish radiculopathy from shoulder disease, peripheral nerve entrapment, and spinal cord compression.
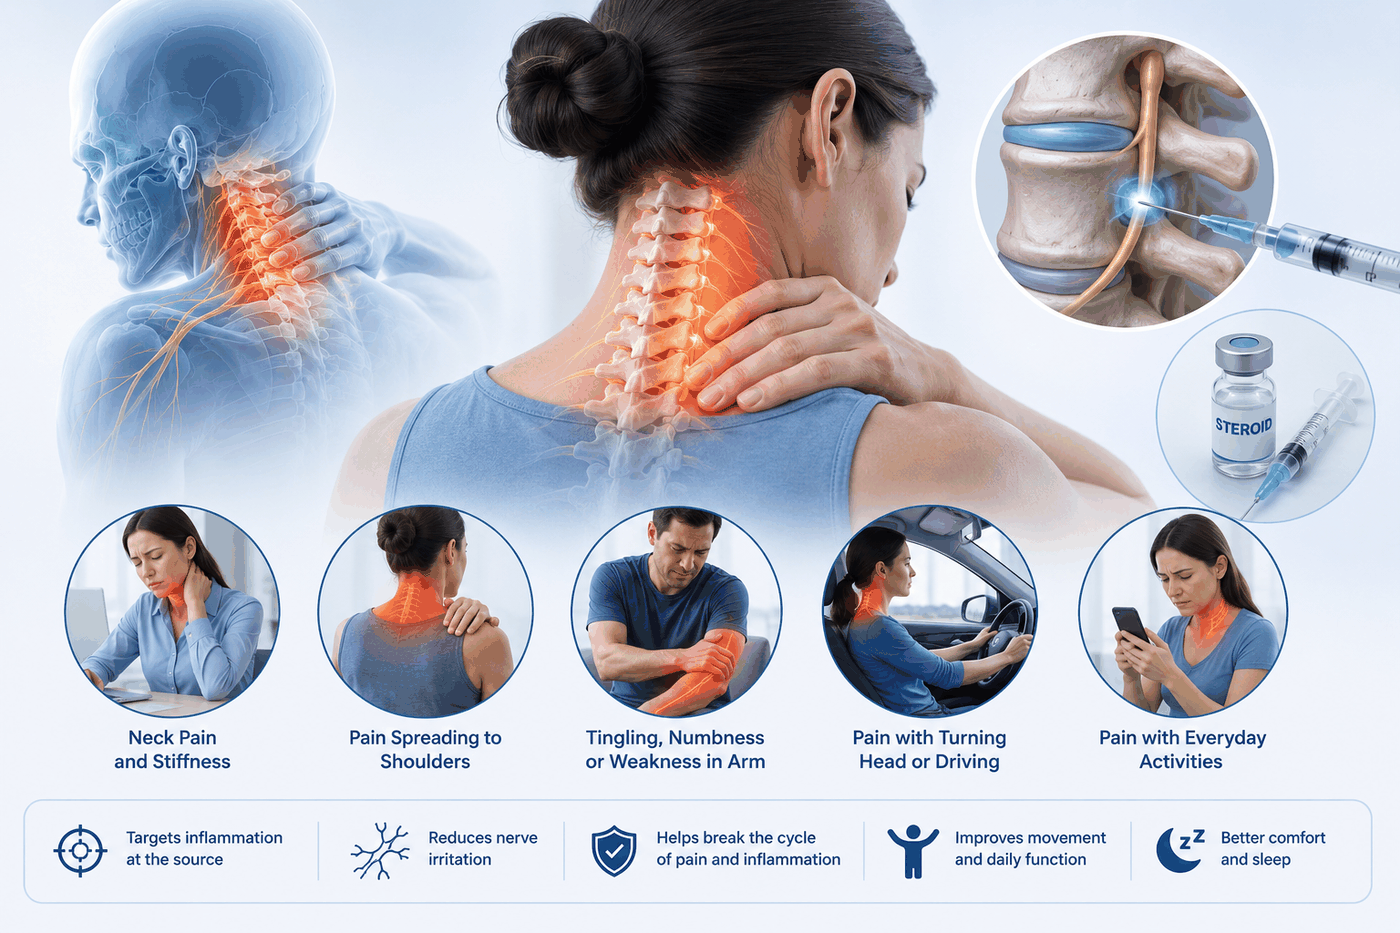
- Neck pain that travels into the shoulder, arm, forearm, or hand
- Burning, electric, stabbing, or shooting arm pain
- Tingling or numbness in a consistent finger distribution
- Pain aggravated by certain neck positions, coughing, or straining
- Reduced grip or weakness in an arm muscle group
- Difficulty sleeping or participating in physical therapy because of arm pain
- Symptoms associated with a disc herniation or foraminal narrowing on imaging
- Persistent radicular pain despite medication and rehabilitation
How Candidacy Is Evaluated
The clinician must distinguish nerve-root pain from cervical myelopathy, fracture, infection, tumor, shoulder disease, and peripheral neuropathy before injection.
History and Functional Goals
Your clinician reviews where symptoms begin, whether pain travels, how long it has been present, what worsens or relieves it, and how it affects walking, work, sleep, and daily activity.
Focused Physical Examination
Strength, sensation, reflexes, movement, tenderness, gait, and nerve-tension signs help distinguish joint, disc, nerve, muscle, and other potential pain sources.
Imaging and Prior Records
MRI, CT, or X-rays are reviewed when results are likely to clarify anatomy or change the plan. Prior procedure reports and treatment responses may also be important.
Medication and Health Review
Blood thinners, diabetes, allergies, infection risk, pregnancy, implanted devices, and other medical conditions are discussed so benefits and risks can be considered safely.
The Cervical Steroid Injection Procedure
The approach and treated level are individualized. Sedation, when used, should still allow appropriate communication and monitoring.
Step 1: Preparation
Medication and fasting instructions are confirmed, monitoring is applied, and the neck or upper-back treatment area is cleaned and numbed.
Step 2: Image-Guided Positioning
Fluoroscopy is used to identify the intended epidural access point or nerve-root target.
Step 3: Contrast Confirmation
A small amount of contrast confirms the expected pattern and helps identify intravascular or incorrect placement before steroid is delivered.
Step 4: Medication Injection
The physician slowly injects corticosteroid, often with saline or local anesthetic, while monitoring symptoms and pressure.
Step 5: Observation
The patient is monitored for numbness, weakness, dizziness, reaction, or other changes and receives written discharge instructions.
After a Cervical Steroid Injection
Temporary soreness or a brief symptom flare can occur. The steroid effect may take several days, and some patients do not obtain meaningful relief.
MedlinePlus describes a typical course after an epidural steroid injection:
- You are watched for 15 to 20 minutes before going home
- Needle-site discomfort usually lasts only a few hours
- Pain may be worse for 2 to 3 days before it begins to improve
- The steroid usually takes 3 to 5 days to work
- Improvement may last weeks to months, but rarely up to a year
First-Day Precautions
Arrange transportation and avoid driving or unsafe activity while sedated, numb, dizzy, or weak. Follow dressing and bathing instructions.
Symptom Timeline
Local anesthetic may produce early temporary change. Steroid response is assessed later and can be gradual, partial, or absent.
Rehabilitation Window
When arm pain improves, physical therapy may progress cervical and shoulder mechanics, nerve mobility, posture, strength, and daily tolerance.
Follow-Up
Track arm pain, numbness, strength, sleep, work, medication use, and activity. Repeat treatment is based on documented benefit and risk, not an automatic series. MedlinePlus notes that most providers limit people to two or three epidural injections per year, partly because injections given too often may weaken spinal bone or nearby muscle.
Potential Benefits and Realistic Expectations
A cervical steroid injection may create time and comfort for recovery, but it is one component of care and does not guarantee avoidance of surgery. MedlinePlus reports that epidural steroid injections provide short-term pain relief in at least one half of the people who receive them.
- Targets inflammation near a specific cervical nerve root
- May reduce radiating arm pain for selected patients
- Can make sleep and rehabilitation more manageable
- Uses an outpatient, image-guided approach
- May provide treatment-response information
- Can be coordinated with medication and physical therapy
Cervical Injection Risks and Urgent Warning Signs
Risks include bleeding, infection, headache, pain flare, medication reaction, elevated blood sugar, nerve injury, spinal cord injury, vascular complication, and rare stroke or paralysis.
- Tell the team about blood thinners, diabetes, infection, pregnancy, allergies, and prior contrast reactions
- Do not stop prescribed anticoagulation without instructions from the responsible clinicians
- Seek immediate care for new severe weakness, loss of coordination, or difficulty walking
- Call promptly for fever, drainage, severe positional headache, or rapidly worsening pain
- New bladder or bowel dysfunction, saddle numbness, or major hand clumsiness needs urgent evaluation
- Injection is not a substitute for surgical assessment when the spinal cord or a nerve is significantly compromised
Call 911 for stroke symptoms, severe weakness, breathing difficulty, loss of consciousness, or another life-threatening emergency.
Cervical Steroid Injection in a Neck Pain Plan
The injection addresses inflammation while the broader plan addresses movement, nerve protection, strength, and the underlying structural diagnosis.
Physical Therapy
A tailored program may improve neck and shoulder mobility, posture, nerve tolerance, strength, and confidence with daily activity.
Medication
Short-term anti-inflammatory, pain, or nerve-modulating medication may be considered based on health risks and response.
Other Diagnostic Sources
Shoulder disease, carpal tunnel syndrome, ulnar neuropathy, and other conditions may need parallel evaluation when symptoms overlap. Neck pain that stays in the neck without traveling into the arm may come from the small spinal joints instead, which are evaluated with facet injections rather than an epidural.
Surgical or Advanced Care
Progressive weakness, myelopathy, instability, or disabling symptoms despite appropriate care may prompt surgical or neuromodulation review.
Find the Source of Your Neck and Arm Pain
California Pain Consultants can review your neurologic symptoms, imaging, treatment history, and goals to determine whether cervical back pain may respond to a cervical steroid injection.
Treatment at California Pain Consultants
Your care team sees patients with neck and arm pain at four San Diego County clinics: Kearny Mesa, Rancho Bernardo, La Mesa, and Chula Vista. Cervical injections are performed under fluoroscopy at the Comprehensive Pain ASC in Rancho Bernardo and the EPC Surgery Center in La Mesa. At your first visit, we examine strength, sensation, and reflexes, review your MRI or order one if needed, and explain whether an injection, therapy, or another approach for your neck pain makes the most sense.
We accept most insurances. Call (858) 571-3630 or request your appointment to book your appointment.
Book Your AppointmentTrusted Information and Related Care
Medical references: CMS: Epidural steroid injections for pain management · NIAMS: Back pain diagnosis and treatment.
Related California Pain resources: Neck pain · Epidural steroid injection · Carpal tunnel.
This article is for general education and does not replace an individualized medical evaluation. Recommendations depend on the diagnosis, health history, current medications, imaging, examination, and personal goals.
Your comprehensive treatment plan is designed to help reduce cervical back pain and get you back into a healthy life.
Imagine if chronic cervical back pain wasn’t holding you back every day. We believe you should be treated the way we would treat our own mom or dad — it’s how we care for every patient.
Frequently Asked Questions About Cervical Steroid Injection
Find clear, medically responsible answers about Cervical Steroid Injection, who may be a candidate, what to expect, and when to contact your healthcare team.
What is a cervical steroid injection, and how does it work?
A cervical epidural steroid injection delivers anti-inflammatory medication into the epidural space near irritated nerves in the neck. Imaging guidance is used to confirm the intended location and medication spread.
What conditions or symptoms may a cervical steroid injection help address?
It may be considered for cervical radiculopathy caused by a disc herniation, foraminal narrowing, or other inflammation around a nerve root, especially when pain travels into the shoulder, arm, or hand. It is less likely to help pain that is purely muscular or caused by a different structure.
Who may be a candidate for a cervical steroid injection?
A candidate has symptoms, examination findings, and imaging that point to a cervical nerve source and has no contraindication such as active infection or unsafe bleeding risk. Because the neck contains critical nerves and blood vessels, careful technique and patient selection are essential.
How should I prepare for a cervical steroid injection?
Review blood thinners, diabetes medicines, allergies, pregnancy, infection, and prior reactions to steroids or contrast with the team. Follow fasting and transportation instructions, and never stop anticoagulant medication without coordinated medical guidance.
What happens during a cervical steroid injection?
The physician positions a needle under fluoroscopic guidance and uses contrast to verify safe epidural spread before medication is delivered. The specific interlaminar or transforaminal approach depends on anatomy, symptoms, and risk assessment.
What is recovery like after a cervical steroid injection?
Temporary neck soreness, arm heaviness, numbness, flushing, headache, or a brief pain increase can occur. Follow discharge instructions, avoid driving until cleared, and resume activity gradually.
Is a cervical steroid injection safe?
Cervical epidural injections are performed with imaging guidance and contrast to improve accuracy, and serious complications are rare. However, the neck contains the spinal cord and major blood vessels, so risks such as infection, bleeding, nerve injury, and rare stroke or paralysis must be discussed. Your physician will review your health history and medications to reduce risk. Possible risks also include dural puncture headache, steroid effects, or allergic reaction.
How long does a cervical steroid injection take to work?
Some people notice brief early relief from the local anesthetic, but the steroid itself usually takes 3 to 5 days to work, according to MedlinePlus. Pain can even be slightly worse for 2 to 3 days before it improves.
How long does relief from a cervical epidural last?
Relief varies. MedlinePlus notes that improvement may last weeks to months, but rarely up to a year, and that at least half of people get short-term relief. The goal is often to calm nerve inflammation enough for physical therapy and natural healing to take over, since many cases of cervical radiculopathy improve over time. The response helps guide rehabilitation or additional evaluation.
How many cervical steroid injections can I have?
There is no single fixed number, but MedlinePlus notes that most providers limit people to two or three epidural injections per year. Repeat injections are based on how much the previous one helped and for how long. If benefit is short or absent, your care team will look at other options rather than repeating the same injection.
Can a cervical injection help me avoid neck surgery?
For some people, yes, but there is no guarantee. By reducing inflammation around a nerve root, an injection may relieve arm pain while the disc or nerve heals on its own. It cannot remove a herniation or bone spur. Progressive weakness, loss of coordination, or signs of spinal cord compression call for a surgical evaluation.
How does a cervical steroid injection fit into a broader treatment plan?
The injection may reduce nerve inflammation enough to support sleep, activity, and physical therapy, but it does not reverse every structural problem. Ongoing care may include posture and movement work, medication review, or surgical evaluation when neurologic compression is significant.
When should I call my healthcare team or seek urgent care after a cervical steroid injection?
Seek immediate care for new or worsening arm or leg weakness, severe unrelenting headache, loss of balance, bowel or bladder changes, chest pain, or breathing difficulty. Also contact the care team promptly for fever, drainage, increasing redness, or rapidly worsening pain.