
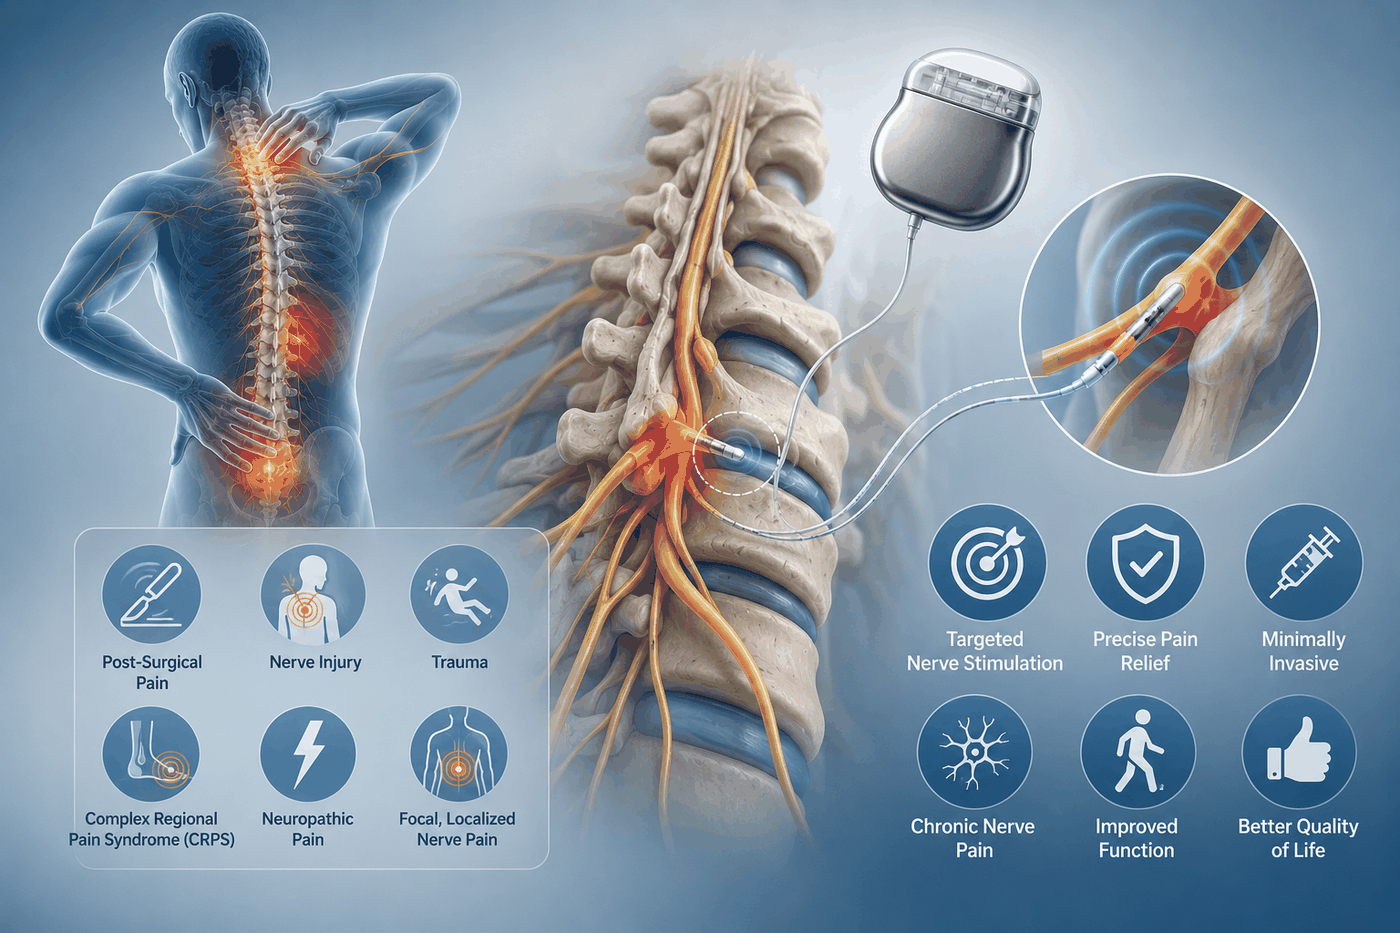
Dorsal root ganglion stimulation is an implantable neuromodulation treatment for carefully selected adults with chronic, focal neuropathic pain. The FDA-approved system targets moderate to severe chronic intractable pain of the lower limbs associated with complex regional pain syndrome types I or II. The board-certified pain specialists at California Pain Consultants in San Diego evaluate candidates for DRG stimulation and guide patients through the trial, implant, and long-term programming.
The dorsal root ganglion is a cluster of sensory nerve-cell bodies near each spinal nerve root. Stimulation at a specific level can focus therapy on a painful region such as the foot, ankle, knee, groin, or another lower-limb distribution.
A temporary trial allows the patient and clinician to measure benefit before considering a permanent implant. The goal is better function and quality of life, not a guarantee of complete pain elimination.
Dorsal root ganglion stimulation uses implanted leads near selected DRGs to modify focal neuropathic pain signals, with a required trial phase before long-term implantation.
What Is Dorsal Root Ganglion Stimulation?
DRG stimulation delivers mild electrical pulses near the sensory gateway that carries information from a defined body region into the spinal cord.
Traditional spinal cord stimulation often covers broader areas. DRG therapy is designed for more focused targeting and may be less affected by body position, although device response varies by patient and programming.
The system includes one or more leads, an implanted pulse generator, and an external controller or programmer. Programming is individualized and may be adjusted over time.
Who May Be a Candidate for DRG Stimulation?
Candidacy is specific and includes diagnosis, prior treatment, psychological and functional evaluation, device safety, and trial response.
CRPS Type I
Complex regional pain syndrome can cause disproportionate regional pain, sensitivity, color or temperature change, swelling, and movement limitation without a confirmed major nerve injury. MedlinePlus notes that CRPS is more common in people ages 40 to 60, although younger people can develop it, and that the outlook is better with early diagnosis.
CRPS Type II / Causalgia
Similar regional symptoms may follow a known nerve injury. DRG stimulation is FDA approved for selected chronic intractable lower-limb CRPS I or II pain.
Focal Lower-Limb Neuropathic Pain
A clearly localized distribution and prior treatment failure may prompt specialist evaluation within device labeling and current evidence.
Successful Trial and Practical Readiness
Permanent implantation is considered only after meaningful trial benefit and the patient demonstrates understanding of device care, follow-up, and realistic goals.
Features of Focal Neuropathic Pain
Neuropathic pain can be severe even when tissue healing appears complete. A full evaluation is needed to confirm the diagnosis and rule out an urgent cause.
- Burning, electric, stabbing, or shooting pain
- Pain from light touch or clothing that would not normally hurt
- Persistent lower-limb pain after injury or surgery
- Swelling, sweating, color, or temperature change in a painful region
- Reduced movement, guarding, stiffness, or weakness
- Pain focused in the foot, ankle, knee, groin, or another defined area
- Major disruption of walking, sleep, work, or self-care
- Inadequate improvement with appropriate multimodal treatment
How Candidacy Is Evaluated
The evaluation confirms the neuropathic diagnosis, identifies the target distribution, and determines whether an implantable therapy is safe and practical.
Diagnosis and Pain Mapping
The clinician maps symptoms, sensory change, autonomic findings, prior nerve injury, surgery, and whether the pattern fits CRPS or another focal neuropathic condition.
Treatment and Function Review
Medication, rehabilitation, blocks, psychological care, and other procedures are reviewed alongside walking, sleep, work, and daily goals.
Medical and Imaging Review
Imaging and testing assess spinal anatomy, infection and bleeding risk, and other conditions that could explain symptoms or affect implantation.
Psychological and Device Assessment
Evaluation addresses coping, expectations, cognition, substance-use risk, support, and the ability to manage charging or controller tasks when applicable.
The DRG Stimulation Trial and Implant
A trial comes first. It provides direct information about target coverage, comfort, function, and whether long-term implantation is reasonable.
Step 1: Baseline Goals
Pain distribution, medication use, walking, sleep, and specific functional goals are documented before stimulation begins.
Step 2: Temporary Lead Placement
Under fluoroscopy, leads are advanced into the epidural space and positioned near selected dorsal root ganglia.
Step 3: External Trial
The leads connect to an external generator. Programming is adjusted while the patient tests normal, safe daily activities and records response.
Step 4: Trial Review
The team evaluates pain change, function, medication, sleep, stimulation comfort, and practical device experience, not pain percentage alone. As a general benchmark, Cleveland Clinic describes moving on to a permanent implant when the trial reduces pain by more than 50%.
Step 5: Permanent Implant When Appropriate
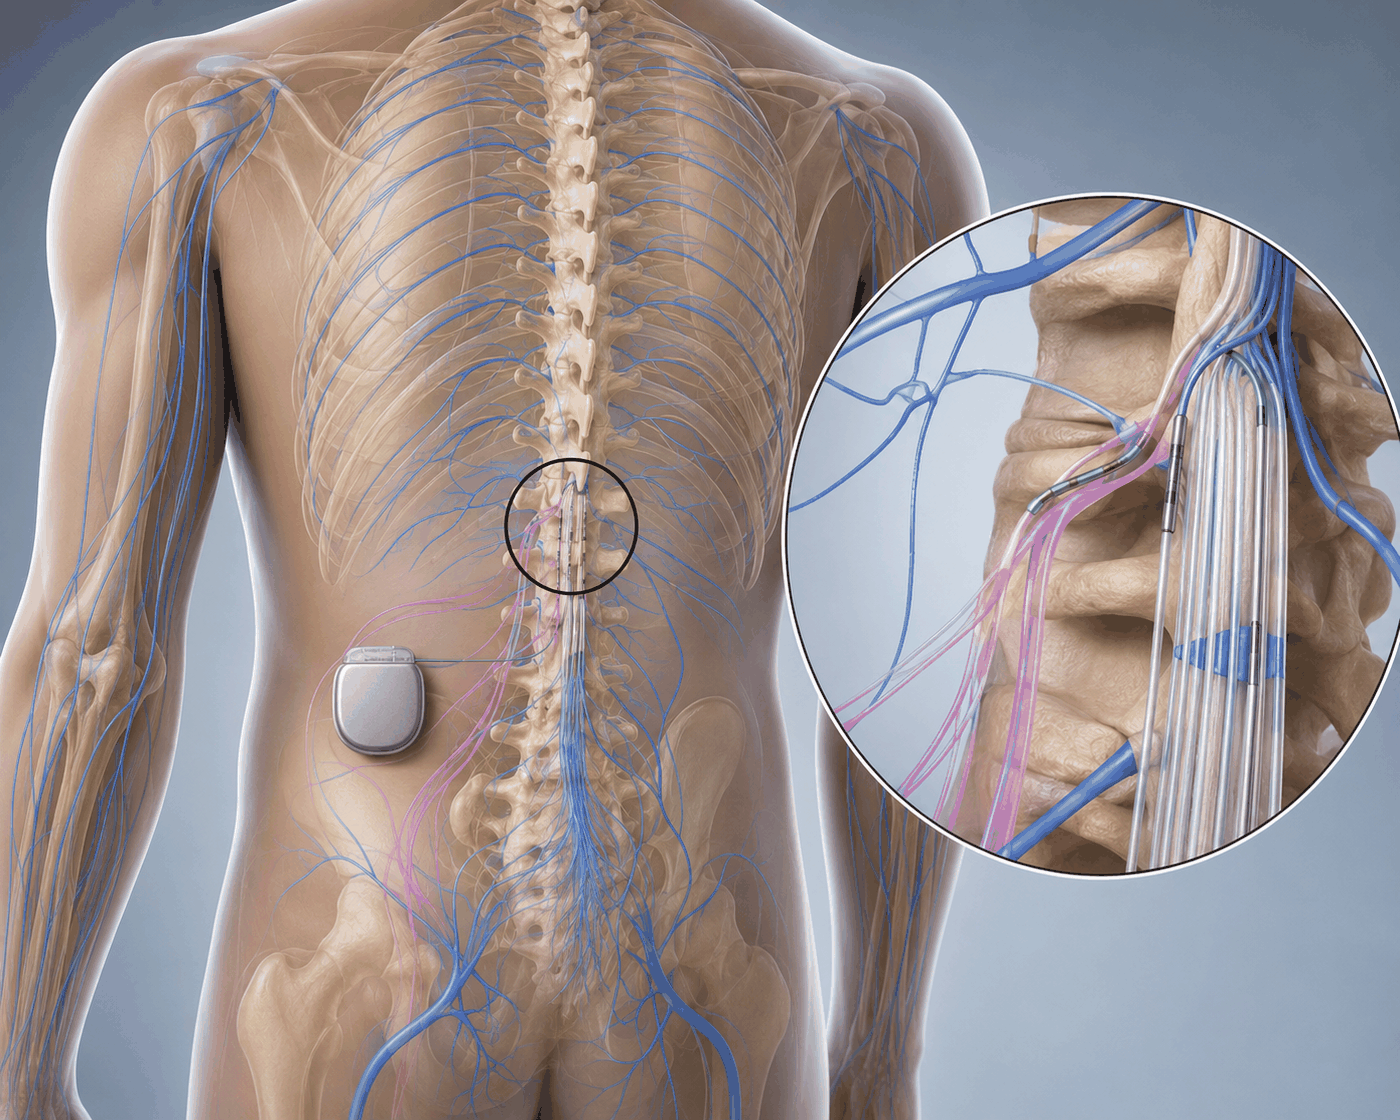
If the trial is successful, permanent leads and an internal pulse generator are implanted, followed by wound care, restrictions, and programming.
Recovery and Life With DRG Stimulation
Early movement restrictions protect lead position and incisions. Ongoing programming and self-management are part of long-term care.
Incision and Lead Protection
Follow restrictions for bending, twisting, lifting, reaching, bathing, driving, and exercise while tissues anchor around the leads.
Programming
Several sessions may be needed to refine coverage and comfort. Contact the team if stimulation becomes unpleasant or benefit changes.
Rehabilitation
A gradual movement and desensitization plan can help translate symptom improvement into walking, strength, confidence, and daily function.
Device Safety
Carry device information and follow current manufacturer instructions for MRI, surgery, security systems, driving, charging, and other equipment. Cleveland Clinic notes that most DRG generators last about six to seven years, and replacing one is a minor outpatient procedure in which the leads usually stay in place.
Potential Benefits and Realistic Expectations
DRG stimulation may provide focused, adjustable therapy for a difficult pain condition, but trial success cannot guarantee the long-term result. In one study cited by Cleveland Clinic, 63% of people still had more than 50% pain relief after one year, which also means a meaningful share of patients did not reach that level.
- Targets selected dorsal root ganglia for focal coverage
- Includes a reversible trial before permanent implantation
- May reduce chronic lower-limb neuropathic pain
- May improve walking, sleep, and daily participation
- Provides adjustable, nondrug pain-signal modulation
- Can be combined with rehabilitation and psychological support
DRG Stimulation Risks and Device Considerations
Risks include bleeding, infection, dural puncture, nerve injury, lead movement or breakage, pain at the implant, hardware malfunction, uncomfortable stimulation, and loss of benefit.
- Tell the team about infection, blood thinners, allergies, pregnancy, and other implanted devices
- Follow all incision care and movement restrictions after trial and implant
- Call for fever, drainage, wound opening, or increasing implant-site pain
- Report sudden loss of stimulation, painful stimulation, or a major change in coverage
- Seek urgent care for new weakness, saddle numbness, or bladder or bowel loss
- Use only MRI and procedure protocols approved for the exact implanted system and configuration
Call 911 for severe weakness, breathing difficulty, loss of consciousness, or another life-threatening emergency.
DRG Stimulation in Comprehensive CRPS Care
Neuromodulation is most useful when it supports a broader plan for movement, desensitization, coping, sleep, and meaningful activity.
Rehabilitation
Graded movement, gait training, desensitization, mirror-based strategies, and functional restoration may help prevent long-term disuse.
Medication
Nerve-pain medication and other agents may be adjusted gradually according to response and side effects. A sympathetic block may also be used in CRPS care, both to help with pain and to support participation in rehabilitation.
Behavioral and Sleep Support
Pain-focused psychological care can improve coping, pacing, sleep, and confidence without suggesting that pain is imagined.
Ongoing Device Care
Programming, battery management, activity planning, and periodic review help maintain safe, useful treatment over time.
See Whether Focused Neuromodulation Fits Your Pain Pattern
California Pain Consultants can evaluate chronic focal neuropathic pain, review prior treatment, and explain the dorsal root ganglion stimulation trial, implant, alternatives, and realistic goals.
Getting DRG Stimulation Care in San Diego
At California Pain Consultants, a DRG stimulation evaluation is unhurried and thorough. Your care team reviews your diagnosis, prior treatments, imaging, and daily goals, and explains how DRG stimulation compares with other options, including conventional spinal cord stimulation, nerve blocks, medication changes, and rehabilitation. If you move forward, trial and implant procedures are performed at the Comprehensive Pain ASC in Rancho Bernardo or the EPC Surgery Center in La Mesa, and programming follow-up continues at the clinic closest to you.
We see patients in Kearny Mesa, Rancho Bernardo, La Mesa, and Chula Vista. We accept most insurances. Request your appointment or call (858) 571-3630 to talk with your care team.
Book Your AppointmentTrusted Information and Related Care
Medical references: FDA: Axium DRG neurostimulator approval · FDA: DRG stimulator product classification.
Related California Pain resources: Complex regional pain syndrome · Neuropathy · Phantom limb pain.
This article is for general education and does not replace an individualized medical evaluation. Recommendations depend on the diagnosis, health history, current medications, imaging, examination, and personal goals.
Frequently Asked Questions
How is DRG stimulation different from spinal cord stimulation?
DRG stimulation targets the dorsal root ganglion, a sensory nerve cluster beside the spinal cord, rather than the spinal cord itself. This allows therapy to be focused on a small, defined area such as a foot, knee, or groin. Conventional spinal cord stimulation usually covers broader regions. Your physician will recommend the approach that best matches your pain map.
What conditions is DRG stimulation approved for?
In the United States, DRG stimulation is FDA approved for moderate to severe chronic intractable lower-limb pain associated with complex regional pain syndrome types I and II. It has also been studied for other focal nerve pain conditions. Your care team will explain whether your diagnosis falls within approved use and what the evidence shows.
How long is the DRG stimulation trial?
The trial usually lasts several days, long enough to test stimulation during normal daily activities. Temporary leads are placed with X-ray guidance and connected to an external generator. You record your pain, sleep, and function, and the results help you and your physician decide whether a permanent implant is reasonable.
Is DRG stimulation reversible?
Yes, DRG stimulation is considered reversible. The trial leads are removed at the end of the trial, and a permanent system can be turned off, reprogrammed, or surgically removed if it stops helping or causes problems. This flexibility is one reason neuromodulation is often discussed before more permanent surgical options.
Will I feel the stimulation?
Many patients feel little or a mild sensation in the targeted area, and programming is adjusted to keep stimulation comfortable. Because DRG stimulation focuses on a specific nerve level, sensation is usually limited to that region. If stimulation becomes uncomfortable or coverage changes, your care team can reprogram the device.
What is recovery like after a permanent DRG implant?
Bandages usually stay on for a few days, and some soreness, swelling, and bruising are normal. You will be asked to avoid rapid twisting, excessive bending, and strenuous activity while the leads anchor in place. Most patients gradually return to normal routines over several weeks with guidance from their care team.