
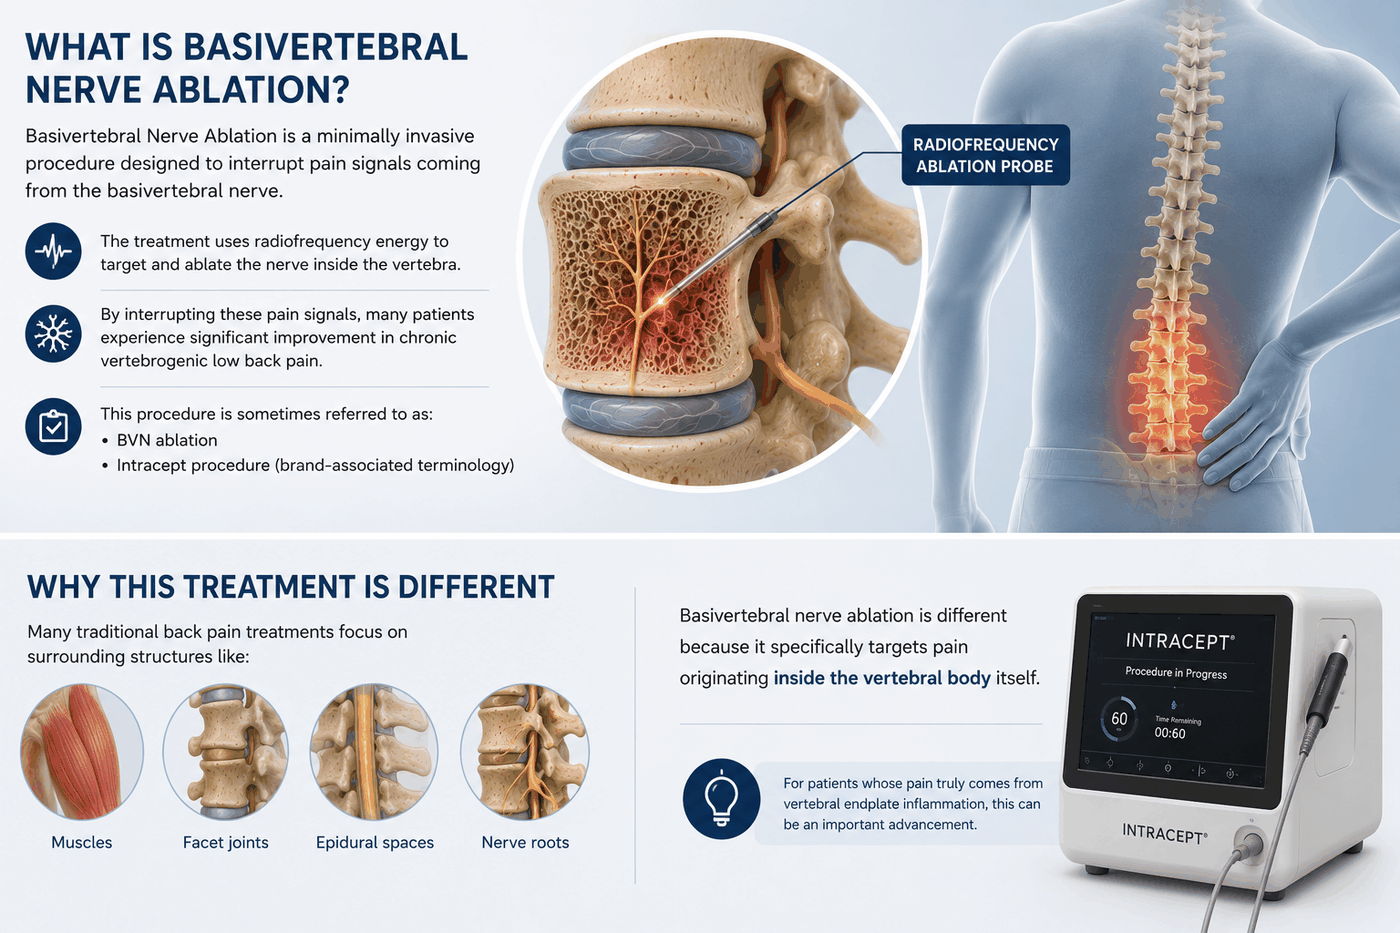
Basivertebral nerve ablation is a minimally invasive, image-guided procedure that uses radiofrequency energy to quiet the nerve that carries pain signals from damaged vertebral endplates. It may help adults with chronic low back pain that is centered in the spine, matches specific MRI findings, and has not improved with conservative care. Board-certified pain specialists at California Pain Consultants in San Diego evaluate candidacy and perform basivertebral nerve ablation for carefully selected patients.
Basivertebral nerve ablation is a minimally invasive treatment for carefully selected adults with chronic vertebrogenic low back pain. This pain is thought to arise from damaged or inflamed vertebral endplates, the interfaces between a spinal disc and the bones above and below it.
The procedure uses radiofrequency energy inside the vertebral body to interrupt signals carried by the basivertebral nerve. It is not intended for every type of low back pain, sciatica, or nonspecific MRI finding.
Candidacy depends on a consistent symptom pattern, Modic type 1 or type 2 endplate changes on MRI, an appropriate duration of pain, and inadequate improvement with a structured conservative plan.
Basivertebral nerve ablation targets the nerve within a vertebral body when clinical findings and MRI changes support vertebrogenic low back pain.
Understanding Vertebrogenic Low Back Pain
Vertebrogenic pain is associated with the vertebral endplates rather than primarily with a compressed nerve root, superficial muscle, or facet joint.
Endplates help transfer load between discs and vertebral bodies. Repeated stress and degeneration can produce inflammation and structural change. The basivertebral nerve supplies these endplates and can transmit pain signals from the affected region.
Chronic low back pain is a large problem with many possible sources. A review published by the American Society of Regional Anesthesia and Pain Medicine (ASRA) notes that chronic low back pain affects over 30 million Americans annually, with up to 80% of cases classified as nonspecific. Identifying a vertebrogenic pattern can give some of those patients a more specific diagnosis.
On MRI, Modic type 1 changes generally reflect edema and inflammation, while type 2 changes reflect fatty marrow replacement. These findings must be interpreted with the history and examination because imaging alone does not establish the diagnosis.
Who May Be a Candidate for Basivertebral Nerve Ablation?
Selection criteria are specific. A clinician should first evaluate other plausible pain sources and contraindications.
Chronic Axial Low Back Pain
Pain is typically centered in the low back, has lasted at least six months, and causes a meaningful functional limitation.
The ASRA review describes the same core selection standard: chronic axial low back pain of at least 6 months’ duration that has not responded to conservative management.
Consistent Clinical Pattern
Symptoms may worsen with sitting, bending, lifting, or sustained spinal loading and are not explained mainly by active nerve-root compression.
Modic Type 1 or 2 Changes
MRI shows compatible endplate changes at an appropriate lumbar level, commonly from L3 through S1 for the referenced device indication.
Conservative Care Has Not Been Enough
A documented trial of appropriate nonoperative treatment has not produced adequate, durable functional improvement.
What Vertebrogenic Pain May Feel Like
There is no single symptom that proves the diagnosis, but the overall pattern can raise or lower suspicion.
- Deep, aching pain centered in the midline low back
- Pain with sitting, bending forward, lifting, or prolonged activity
- Symptoms that may spread toward the buttocks without a clear nerve-root pattern
- Morning stiffness or pain during transitions such as rising from a chair
- Persistent limitation despite physical therapy and appropriate medication
- MRI evidence of compatible vertebral endplate changes
How Candidacy Is Evaluated
The evaluation separates suspected vertebrogenic pain from facet, sacroiliac, muscular, hip, disc, stenotic, fracture, infection, and nerve-root causes.
History and Functional Goals
Your clinician reviews where symptoms begin, whether pain travels, how long it has been present, what worsens or relieves it, and how it affects walking, work, sleep, and daily activity.
Focused Physical Examination
Strength, sensation, reflexes, movement, tenderness, gait, and nerve-tension signs help distinguish joint, disc, nerve, muscle, and other potential pain sources.
Imaging and Prior Records
MRI, CT, or X-rays are reviewed when results are likely to clarify anatomy or change the plan. Prior procedure reports and treatment responses may also be important.
Medication and Health Review
Blood thinners, diabetes, allergies, infection risk, pregnancy, implanted devices, and other medical conditions are discussed so benefits and risks can be considered safely.
The Basivertebral Nerve Ablation Procedure
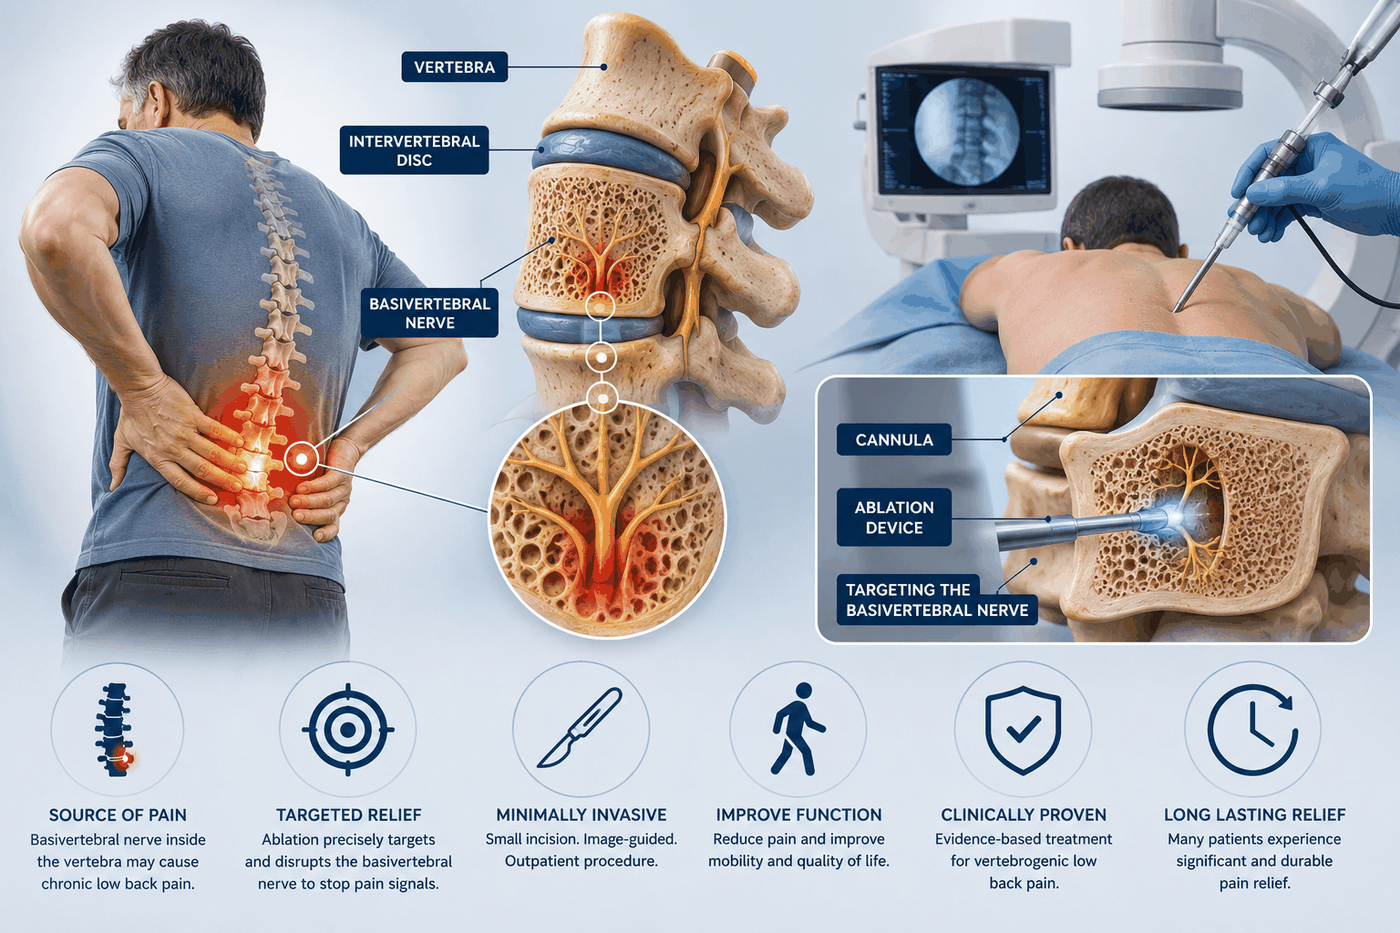
The procedure is performed with sterile technique and imaging guidance. Details depend on the device, treated levels, and patient-specific plan.
Step 1: Preparation and Anesthesia
Preprocedure instructions are reviewed, monitoring is applied, and anesthesia or sedation is provided according to the treatment plan.
Step 2: Vertebral Access
A small access channel is created through the pedicle or another approved route into the target vertebral body under fluoroscopic guidance.
Step 3: Probe Positioning
A curved instrument and radiofrequency probe are advanced toward the basivertebral nerve location within the bone.
Step 4: Radiofrequency Treatment
Controlled energy heats the target region to interrupt basivertebral nerve signaling while the physician monitors positioning.
Step 5: Completion and Observation
The instruments are removed, the small access site is dressed, and the patient is observed before discharge with written instructions.
Recovery After Basivertebral Nerve Ablation
This is not always an immediate-relief procedure. Some patients notice gradual change over weeks as procedural soreness settles and activity is rebuilt.
Early Soreness
Temporary incisional or deep back soreness can occur. Use only the medications and wound-care steps recommended by the treating team.
Activity Progression
Walking and light activity may resume first, followed by gradual return to lifting, exercise, and work according to individual instructions.
Rehabilitation
Physical therapy may address strength, mobility, movement habits, endurance, and confidence as symptoms allow.
Outcome Review
Follow-up considers pain, sitting and walking tolerance, sleep, medication use, work, and goal-specific function over time.
Potential Benefits and Realistic Expectations
For appropriately selected patients, the procedure offers a focused treatment for an endplate-related pain mechanism. Results vary and are not guaranteed.
- Targets a defined nerve inside the vertebral body
- Uses a minimally invasive, image-guided approach
- Preserves the overall structure of the spine
- May improve pain and function in selected vertebrogenic cases
- Can complement rehabilitation and activity restoration
- Offers an option between conservative care and more extensive surgery
Results and How Long Relief May Last
Because the treated nerve sits inside bone, basivertebral nerve ablation is intended to provide durable relief rather than a short-term effect. Published long-term data are encouraging for selected patients, though individual results vary.
- In a 5-year pooled analysis of 249 participants summarized by ASRA, 32.1% reported complete pain relief and 72.7% reported improvement in their condition.
- The same analysis reported that 65.2% of participants who used opioids before treatment had stopped them.
- Improvement often develops over weeks as procedural soreness settles and activity is rebuilt.
- Results depend on accurate selection, so the procedure is not offered for pain that comes mainly from facet joints, nerve roots, or the sacroiliac joint.
Risks, Contraindications, and Warning Signs
Possible risks include bleeding, infection, temporary pain increase, nerve injury, bone or access-tract injury, anesthesia complications, and failure to improve. Device-specific contraindications also apply.
- Review osteoporosis, fracture history, infection, cancer, pregnancy, and bleeding risk
- Tell the team about blood thinners, allergies, implanted devices, and prior spine surgery
- Call for fever, drainage, wound opening, or spreading redness
- Seek urgent care for new weakness, saddle numbness, or bladder or bowel loss
- Report severe or rapidly escalating back or leg pain
- Alternative pain sources should be addressed when the clinical pattern is not vertebrogenic
- ASRA notes that rare vertebral compression fractures have been reported in patients with preexisting osteoporosis
Call 911 for major new neurologic symptoms, breathing difficulty, loss of consciousness, or another life-threatening emergency.
Basivertebral Nerve Ablation in Comprehensive Spine Care
The procedure addresses one specific pain generator and should sit within a broader plan for health, movement, and long-term function.
Rehabilitation
Strength, mobility, graded loading, and movement coaching remain important even when the procedure reduces the endplate-related pain signal.
Medication Review
Medication may be used short term or adjusted over time based on response, health conditions, and side effects.
Other Interventions
Facet treatment, epidural injection, sacroiliac care, or another procedure may be more appropriate when evaluation identifies a different pain source.
Surgical Consultation
Instability, severe stenosis, fracture, tumor, progressive neurologic deficit, or deformity may require a separate surgical or specialty evaluation.
Is Your Low Back Pain Vertebrogenic?
California Pain Consultants can review your symptom pattern, MRI findings, treatment history, and goals to determine whether basivertebral nerve ablation or another pathway deserves consideration.
Treatment at California Pain Consultants
At California Pain Consultants, your evaluation looks for the specific pattern that suggests vertebrogenic pain: midline low back pain that worsens with sitting and bending, has lasted at least six months, and lines up with Modic changes on MRI. Your care team also checks for other common sources, such as facet joints, which may respond to facet injections or standard radiofrequency ablation, and the sacroiliac joint, which may respond to sacroiliac joint injections. If basivertebral nerve ablation fits, your team explains the procedure, recovery, and realistic goals before scheduling.
We see patients at four clinics across San Diego County:
San Diego, CA 92123Get Directions
San Diego, CA 92128Get Directions
La Mesa, CA 91942Get Directions
Chula Vista, CA 91911Get Directions
Procedures are performed at the Comprehensive Pain ASC in Rancho Bernardo and the EPC Surgery Center in La Mesa. We accept most insurances. Call (858) 571-3630 or request your appointment to have your MRI and symptoms reviewed.
Book Your AppointmentTrusted Information and Related Care
Medical references: FDA: Intracept 510(k) summary · NIAMS: Back pain diagnosis and treatment.
Related California Pain resources: Low back pain · Degenerative disc disease · All treatment options.
This article is for general education and does not replace an individualized medical evaluation. Recommendations depend on the diagnosis, health history, current medications, imaging, examination, and personal goals.
Frequently Asked Questions
What is vertebrogenic low back pain?
Vertebrogenic low back pain is chronic pain that comes from damaged or inflamed vertebral endplates, the surfaces where each disc meets the bone above and below it. The basivertebral nerve carries these pain signals. It typically causes deep, midline low back pain that worsens with sitting, bending, or lifting and is linked to Modic changes on MRI.
How do I know if I am a candidate for basivertebral nerve ablation?
Candidates usually have chronic low back pain centered in the spine for at least six months, Modic type 1 or type 2 changes at a matching lumbar level, and inadequate improvement after conservative care such as physical therapy and medication. Your care team reviews your MRI, examination, and history to rule out other pain sources first.
How long does relief from basivertebral nerve ablation last?
The procedure is designed for long-lasting relief. In a 5-year pooled analysis summarized by ASRA, about 73% of participants reported improvement and about one in three reported complete pain relief. Individual results vary, improvement may build over weeks, and continued rehabilitation helps you get the most from treatment.
Is basivertebral nerve ablation the same as radiofrequency ablation for facet pain?
Both use radiofrequency energy, but they target different nerves. Facet radiofrequency ablation treats small medial branch nerves outside the spine that carry pain from the facet joints. Basivertebral nerve ablation reaches a nerve inside the vertebral body that carries pain from the endplates. Each treats a different pain source, so diagnosis determines which fits.
What is recovery like after basivertebral nerve ablation?
Most patients go home the same day. Soreness at the access sites or deep in the back is common for several days. Walking and light activity usually resume first, followed by a gradual return to lifting, exercise, and work. Your care team gives individual instructions and may recommend physical therapy to rebuild strength and endurance.
Is basivertebral nerve ablation FDA cleared?
Yes. The FDA 510(k) clearance for the Intracept system covers ablation of basivertebral nerves from L3 through S1 for chronic low back pain lasting at least six months that has not responded to at least six months of conservative care and shows Modic type 1 or type 2 features on MRI. Clearance does not guarantee individual results.